Trigger Points Explained: Why Muscle Knots Refer Pain
Why a knot in your shoulder can give you a headache, what science actually knows about trigger points, and what helps.
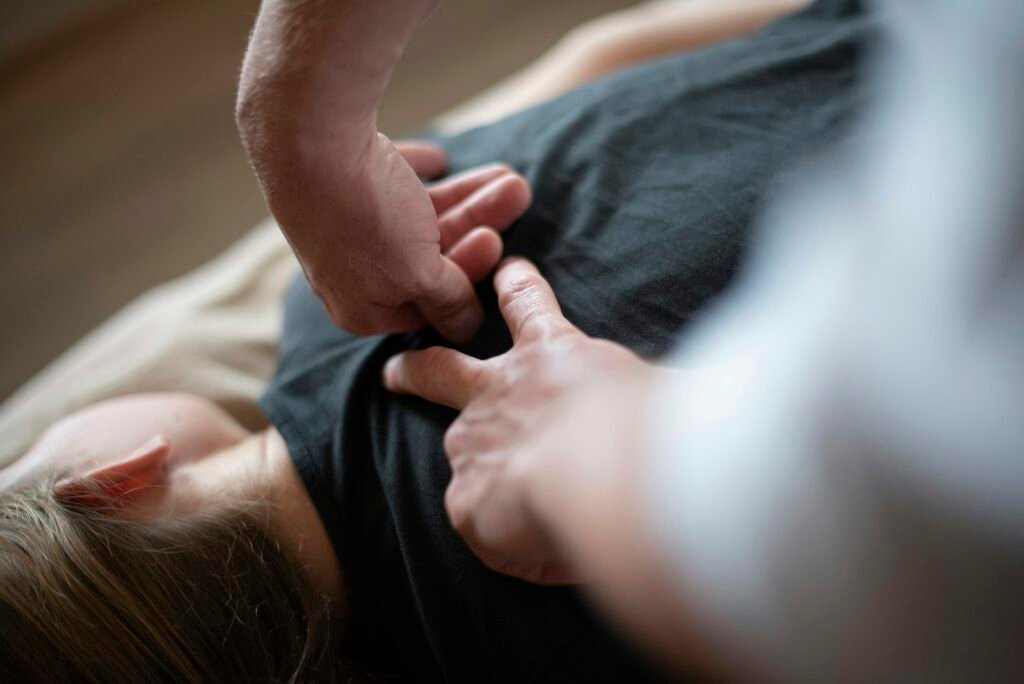
A trigger point is a small, very tender spot inside a tight band of muscle, the thing most people call a “knot”. Pressing on it often causes pain somewhere else, not just where you press: a spot in the top of the shoulder can send an ache up the side of the neck towards the temple, for example. That spreading pain is called referred pain. It happens because nerve signals from muscle meet other nerve signals in the spinal cord, and the brain can’t always tell exactly where the pain started. Trigger points are commonly treated with pressure, stretching, exercise and dry needling, though researchers still debate exactly what they are.
The short version
- A trigger point is a sensitive spot in a taut band of muscle. Experts agree on three key features: the taut band, the tender spot, and pain felt elsewhere when it’s pressed.
- Referred pain is real and well studied. Irritating a muscle in the lab can cause pain in a completely different area.
- The pain may not be where the problem is. Neck and shoulder muscles can contribute to headaches, and hip muscles can cause pain down the leg.
- The science is still debated. Examiners don’t always agree on where trigger points are, and some researchers question the theory behind them.
- Treatment is usually simple: pressure, movement, strengthening and sometimes dry needling, as part of a wider plan.
What is a trigger point?
When people talk about a muscle “knot”, they usually mean a myofascial trigger point. In 2018, a panel of 60 international experts agreed on three features needed to identify one:1
- A taut band: a cord-like, tight strip within the muscle that you can feel under the fingers.
- A hypersensitive spot: one point along that band that is much more tender than the muscle around it.
- Referred pain: pressing the spot causes a sensation somewhere else, which may be a dull ache, deep pain, tingling or burning.
The same panel described two kinds. An active trigger point reproduces pain you already recognise, the ache that’s been bothering you. A latent trigger point is tender when pressed but isn’t part of your usual pain.1 Many people have latent trigger points without any symptoms at all.
Why does a knot cause pain somewhere else?
Referred pain from muscle has been studied for decades. In one classic type of experiment, researchers inject a small amount of salty water into a muscle in the shin. People feel pain in the muscle itself, but also at the front of the ankle, an area that wasn’t touched at all.2
The leading explanation lies in the spinal cord. Nerve fibres carrying signals from different areas, such as a muscle and a patch of skin some distance away, meet at the same nerve cells in the spinal cord. When a muscle sends a strong or prolonged pain signal, those nerve cells can become more sensitive, and the brain reads part of the signal as coming from the other area.3 That’s why the place that hurts isn’t always the place that needs treatment.
There’s also a chemical side. In a small study, researchers sampled the fluid around muscle fibres in the upper trapezius, the muscle across the top of the shoulder. In people with neck pain and active trigger points, the area was more acidic and had higher levels of substances linked to pain and inflammation than in people with no trigger points or with symptom-free ones.4 Those substances are known to make muscle pain receptors more sensitive to pressure.5
Common referral patterns
Clinicians often use maps of typical referral patterns, built up over decades of clinical observation.6 Some of the more familiar ones:
| Muscle | Where the knot is | Where you may feel it |
|---|---|---|
| Upper trapezius | Top of the shoulder | Side of the neck, behind the ear, towards the temple |
| Suboccipitals | Base of the skull | Back and side of the head, behind the eye |
| Infraspinatus | Shoulder blade | Front and side of the shoulder, sometimes down the arm |
| Quadratus lumborum | Lower back, beside the spine | Hip, buttock, sometimes the side of the pelvis |
| Gluteus minimus | Deep in the side of the buttock | Down the back or side of the thigh and calf |
These maps are a guide, not a rule. The expert consensus panel agreed that no specific location of referred pain should be expected for a given trigger point, because patterns vary from person to person.1
When leg pain isn’t coming from the back
Pain down the side or back of the leg from a buttock muscle can feel a lot like sciatica, which comes from an irritated nerve. A careful assessment helps tell them apart. Our guide to sciatica or lower back pain explains the differences.
What causes trigger points?
The exact cause isn’t settled, but trigger points are commonly linked to muscle overload, either sudden (lifting something awkwardly) or sustained (holding the same posture for hours).7 Things that often go along with them include:
- Long hours at a desk or on a phone, with the shoulders and neck held in one position (the pattern behind tech neck)
- Repetitive tasks or a sudden increase in training
- Recovering from an injury, when nearby muscles work harder to protect the area
- Stress, poor sleep and general tension, which can keep muscles guarded
If desk work is part of the picture, our article on lower back pain from sitting all day has simple ways to break up long periods of sitting.
The debate: are trigger points real?
It’s worth being honest about the science. Trigger points are widely used in clinical practice, but they are also contested.
- Agreement between examiners is inconsistent. A review of nine studies found that clinicians agreed fairly well on whether a spot was tender and reproduced pain, but much less on objective signs like the taut band and the muscle twitch.8
- Some researchers reject the theory. A 2015 critical review argued that the idea of trigger points as damaged spots in muscle lacks scientific support, while agreeing that the pain and tenderness people feel are real and can be explained by how the nervous system processes pain.9
For you as a patient, the practical point is this: the tender spots and referred pain are real experiences. What’s still debated is the exact mechanism behind them. A good clinician treats the whole picture, including movement, load, sleep and stress, rather than chasing a single spot.
How trigger points are treated
- Sustained pressure. Firm, steady pressure on the tender spot for 30 to 90 seconds, by a clinician or with a ball against a wall, often eases tenderness for a while.
- Stretching and movement. Gentle stretching and regular movement help keep the muscle from staying guarded.
- Strengthening. Building strength in the overloaded muscle and the muscles around it reduces how hard it has to work, which matters most for stopping the pain coming back.
- Dry needling. A physiotherapist inserts a fine needle into the trigger point. A review of 13 trials found that dry needling by physical therapists may reduce pain in the short term, up to 12 weeks, compared with sham or other treatments, though the long-term benefit was less clear.10
- Looking at the cause. Changing how you sit, train or work, and managing stress and sleep, so the same muscle doesn’t keep getting overloaded.
If you’re curious about needling, read does dry needling hurt? and our guide to dry needling aftercare. You can see how needling fits into a wider plan on our dry needling in Dubai page.
Trying self-massage at home
- Place a tennis or massage ball between the tender spot and a wall.
- Lean in gently until you feel firm pressure, no more than about 6 out of 10 discomfort.
- Hold for 30 to 60 seconds while breathing slowly. The tenderness often eases a little.
- Follow with a gentle stretch or a few easy movements for that muscle.
Avoid pressing directly on bone, the front or sides of the neck, or any area that tingles, goes numb or feels sharp.
Not every ache is a muscle knot. Get checked if you have
- Pain with fever, unexplained weight loss or night sweats
- Numbness, weakness or pins and needles that’s getting worse
- A sudden, severe headache, or a headache with confusion, vision changes or a stiff neck
- Chest, jaw or arm pain with breathlessness or sweating
- Pain after a fall or accident
In the UAE, call 998 for an ambulance in an emergency.
Frequently asked questions
What is the difference between a muscle knot and a trigger point?
They usually mean the same thing. “Knot” is the everyday word; “myofascial trigger point” is the clinical term for a tender spot in a tight band of muscle that can cause pain elsewhere when pressed.
Can trigger points cause headaches?
Trigger points in neck and shoulder muscles, such as the upper trapezius and the muscles at the base of the skull, commonly refer pain to the side or back of the head and the temple. They can contribute to tension-type headaches, but a sudden or severe headache needs medical assessment.
Can a trigger point feel like sciatica?
Yes. Trigger points in deep buttock muscles can send pain down the back or side of the leg, similar to sciatica. A physiotherapy assessment can help tell muscle-referred pain from nerve pain.
How long do trigger points take to go away?
It varies. Some ease within days with pressure and movement. Others keep coming back until the cause, such as posture, overload, sleep or stress, is addressed and the muscle is strengthened.
Is dry needling good for trigger points?
Research suggests dry needling by a physiotherapist may reduce pain in the short term compared with sham or other treatments. It works best as part of a wider plan that includes exercise and changes to what’s overloading the muscle.
References
- Fernández-de-las-Peñas C, Dommerholt J. International consensus on diagnostic criteria and clinical considerations of myofascial trigger points: a Delphi study. Pain Med. 2018;19(1):142-150.
- Graven-Nielsen T, Arendt-Nielsen L, Svensson P, Jensen TS. Stimulus-response functions in areas with experimentally induced referred muscle pain: a psychophysical study. Brain Res. 1997;744(1):121-128.
- Arendt-Nielsen L, Svensson P. Referred muscle pain: basic and clinical findings. Clin J Pain. 2001;17(1):11-19.
- Shah JP, Danoff JV, Desai MJ, et al. Biochemicals associated with pain and inflammation are elevated in sites near to and remote from active myofascial trigger points. Arch Phys Med Rehabil. 2008;89(1):16-23.
- Graven-Nielsen T, Mense S. The peripheral apparatus of muscle pain: evidence from animal and human studies. Clin J Pain. 2001;17(1):2-10.
- Donnelly JM, Fernández-de-las-Peñas C, Finnegan M, Freeman JL. Travell, Simons & Simons’ Myofascial Pain and Dysfunction: The Trigger Point Manual. 3rd ed. Philadelphia: Wolters Kluwer; 2019.
- Simons DG. Review of enigmatic MTrPs as a common cause of enigmatic musculoskeletal pain and dysfunction. J Electromyogr Kinesiol. 2004;14(1):95-107.
- Lucas N, Macaskill P, Irwig L, Moran R, Bogduk N. Reliability of physical examination for diagnosis of myofascial trigger points: a systematic review of the literature. Clin J Pain. 2009;25(1):80-89.
- Quintner JL, Bove GM, Cohen ML. A critical evaluation of the trigger point phenomenon. Rheumatology (Oxford). 2015;54(3):392-399.
- Gattie E, Cleland JA, Snodgrass S. The effectiveness of trigger point dry needling for musculoskeletal conditions by physical therapists: a systematic review and meta-analysis. J Orthop Sports Phys Ther. 2017;47(3):133-149.

About Somatic Recovery
Somatic Recovery is the Dubai practice of Shubhangii Gaikwaad, DHA-Licensed Physiotherapist (MPT, Neurology) with 16 years of clinical experience. Sessions in person in Dubai and online worldwide, in English and Hindi.
This article is general information, not a diagnosis or a substitute for an individual assessment. If you have severe, sudden or worsening symptoms, see a doctor.
Somatic Recovery · Dubai & online
Want this looked at properly?
One assessment with a DHA-licensed physiotherapist to understand what is driving your symptoms, with a clear plan and an honest timeline.
Keep reading
 Dry NeedlingIs Dry Needling Safe? Side Effects, Risks and Who Should Avoid ItMinor soreness is common, serious problems are rare. What the research says about dry needling safety and who needs extra care.6 min read→
 Dry NeedlingDry Needling for Neck Pain and Headaches: Does It Work?Short-term relief for neck pain, promising but less certain for headaches. What the research says and how it fits with exercise.7 min read→
 Dry NeedlingHow Many Dry Needling Sessions Do You Need?There is no magic number. What the research says about how many sessions, how often, and when to change the plan.6 min read→